


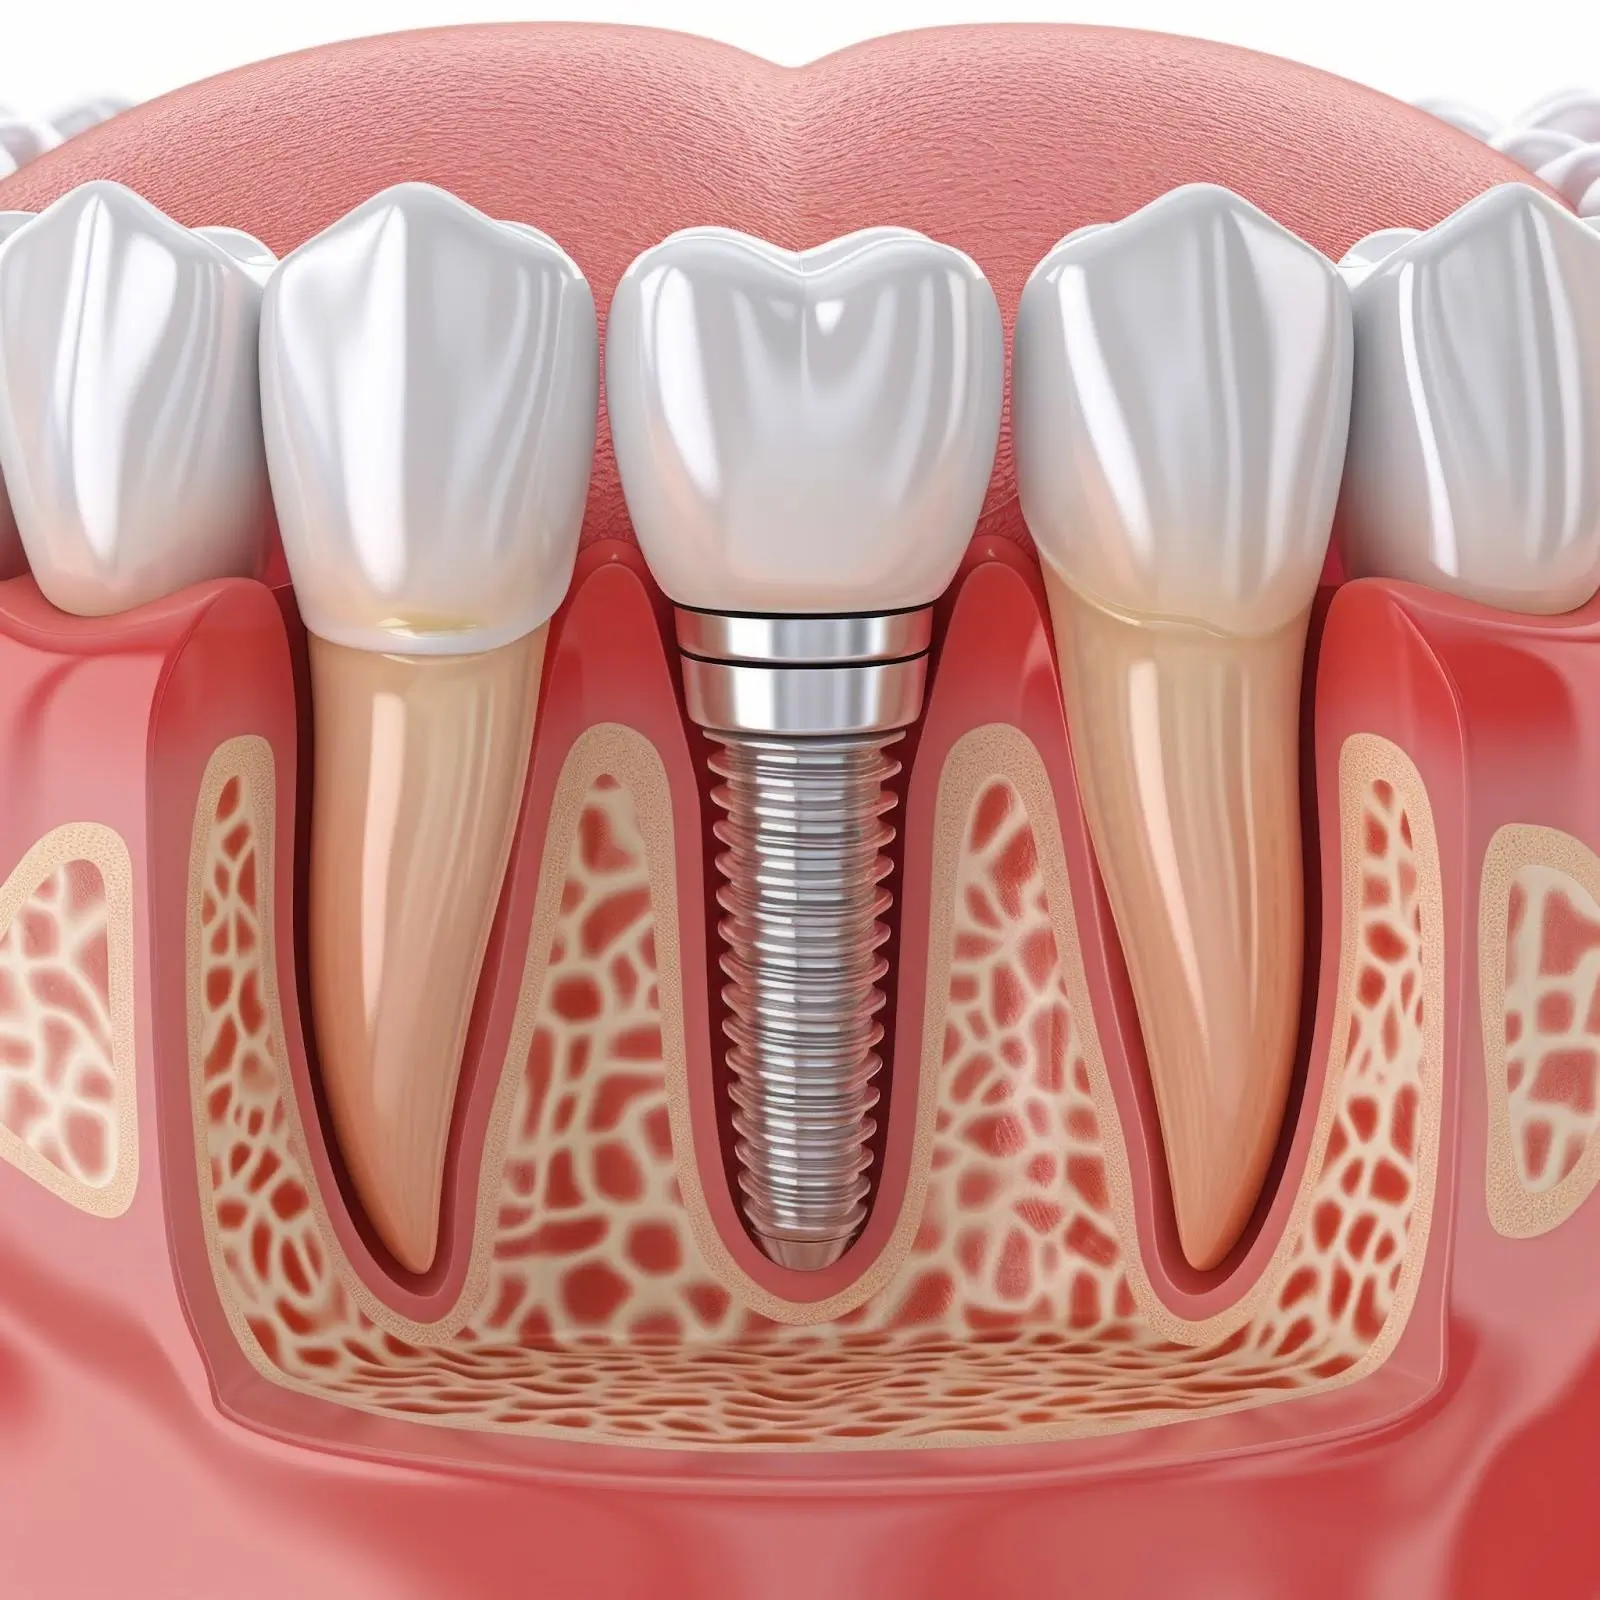
A dental implant does not hold because it is screwed in tightly. It holds because living bone grows onto its surface and locks it in place. That biological process is called osseointegration, and it is the single thing that decides whether an implant lasts three years or thirty.
Everything else in implant dentistry exists to serve it. The scan, the planning software, the drill, the healing period, the timing of the crown. All of it is in service of getting bone to attach to titanium and stay attached.
What Is Osseointegration?
Osseointegration is the direct structural and functional connection between living bone and the surface of a load-bearing implant, with no soft tissue in between. Bone cells attach themselves directly onto the implant surface rather than forming a fibrous layer around it.
That distinction matters more than it sounds. If fibrous tissue forms at the bone implant interface instead of bone, the implant is not integrated. It may feel solid at first, but it has no biological anchorage and it will loosen. Early endosseous implants failed for exactly this reason, decades before anyone understood why.
The word describes what happens at a microscopic level: new bone formation directly onto the titanium implant, growth of bone across the surface of the implant, and a bone structure that treats the implant as part of itself.
Who Discovered Osseointegration?
Per-Ingvar Brånemark, a Swedish orthopedic surgeon, found it by accident in the 1950s. He was studying blood flow in rabbit bone using titanium observation chambers, and when the study ended he could not remove them. The bone had fused to the metal.
He spent the following two decades proving the effect was reliable and could be reproduced in people. The development of osseointegration from that observation into a predictable clinical procedure is the foundation of osseointegration in clinical dentistry, and it also produced bone-anchored hearing aids and osseointegrated limb prostheses.
Brånemark’s original criteria for success are still the ones we measure against, and knowledge about osseointegration has grown steadily since.
How Does The Osseointegration Process Work?
The process called osseointegration begins the moment the implant is inserted into the jaw and runs in overlapping phases rather than clean stages.
- Blood clot and protein layer. Within minutes, blood surrounds the implant and proteins coat the surface of the implant. This layer determines which cells arrive next.
- Cell recruitment. Bone cells migrate to the implant site along the clot scaffold. Blood supply to the surrounding bone governs how many arrive and how quickly.
- New bone formation. Osteoblasts lay down woven bone directly onto the implant surface. This is the point at which biological attachment actually begins, and bone cells attach themselves directly to the titanium.
- Remodeling. The initial woven bone is gradually replaced with organized, load-bearing bone. Bone quality at the implant site improves over months, not weeks.
Titanium is widely used as an implant material because it is biocompatible and because it forms an oxide layer that living bone tissue will attach to. The chemical composition of the implant interface and the growth of bone onto the implant surface are both governed by that oxide layer.
Modern dental implant systems are textured at a microscopic scale to increase the contact area between bone and the implant. There has been great interest in implant surface modification for this reason, and implant surface treatment was shown to influence how quickly bone integrates. Some coated implants use hydroxyapatite for the same purpose. Factors such as surface energy also affect how well the implant bonds.
Primary And Secondary Stability
This is the part almost no one explains to patients, and it is the reason the healing period is not a straight line.
When an implant is inserted, it is held by primary stability: pure mechanical grip between the implant threads and the bone that was there already. Nothing biological has happened yet.
Over the following weeks the body remodels that bone. The original mechanical grip loosens as old bone is resorbed, while new bone has not yet fully formed. Measured implant stability dips, typically around the two to four week mark, before secondary stability from new bone growth takes over and carries it higher than where it started.
An implant is at its most vulnerable at the bottom of that dip. It is why we do not load every implant immediately after implant placement, and why the ones we do load immediately are chosen on the strength of the initial grip and splinted so that no single implant takes the force alone.
Can You Feel Osseointegration Happening?
No. There is no sensation associated with bone growing around the implant, and patients should not expect one.
This surprises people, because the process sounds like it should feel like something. It does not. Bone remodeling produces no nerve signal. Once the initial surgical healing has settled, a well-integrating implant feels like nothing at all.hwo lo
What you can feel is a problem. Persistent throbbing, a pressure ache that returns after settling, or any sense of movement around the implant site are worth a call to us on (347) 493-2439. An integrating implant is silent. A failing one is not.
How Do You Know When Osseointegration Is Complete?
We measure it. We do not guess it, and we do not go purely by the calendar.
Clinically, successful osseointegration is confirmed by a combination of things: the implant is completely immobile under testing, radiographs show living bone in direct contact with the surface of the implant with no radiolucent line around the implant, there is no discomfort under pressure, and the tissue around the implant is healthy.
We also measure stability directly with an implant stability quotient (ISQ) reading, taken with an Osstell device. This is worth separating from insertion torque, which is often quoted as though it were the same measurement. Torque records how hard the implant was to turn as it went in. It is a single number, available once, describing the mechanical grip of bone that was already there. An ISQ reading can be taken again at review, and again after that. Torque describes the starting point; ISQ describes the direction of travel, and it is the only one of the two that can show the stability dip bottoming out and recovering.
Taking a reading at placement and again at review is what tells you the implant has fully integrated rather than simply that time has passed. Comparing a patient’s own readings over time is more informative than any single number, because the starting point varies with bone quality and site.
How Long Does Osseointegration Take?
At our practice the standard healing period is about three months, though the real window depends on where the implant is and what it was placed into.
What moves it:
- Dense lower-jaw bone tends to integrate at the faster end
- Softer upper-jaw bone can need longer
- Sites that needed a bone graft add the graft’s own healing time before the implant clock starts, usually around three months
- Smoking, uncontrolled diabetes and some medications extend it
Immediate loading, where a provisional restoration goes on immediately after implant placement, does not shorten the process. It is not a faster fusion. It means a temporary tooth is carried on the implant while integration proceeds underneath, on the strength of the initial mechanical grip. The biology takes as long as it takes.
We would rather give a patient an accurate window for their own case than a tidy number that applies to a textbook.
What Is The Number One Reason Dental Implants Fail?
It depends entirely on when the implant fails, and the two situations have almost nothing in common.
Early failure means osseointegration never happened. The implant was inserted and bone did not attach. This usually shows up in the first few months, and the causes are surgical and biological: the implant host site was compromised, primary stability was inadequate, the site became infected, or the bone was damaged during preparation.
Late failure means osseointegration happened and was then lost. The implant integrated, functioned, and then bone loss around the implant destroyed it, most often through peri-implantitis, an inflammatory condition driven by bacteria. This is a periodontal disease process, which is why periodontists are the specialists who treat it.
Across both categories, success rates with oral implants are consistently reported above ninety-five percent over ten years. Implant failure is uncommon. But conflating the two types is how patients get the wrong treatment, and a failed dental implant is worth a second opinion before anything is removed.
Heat During Placement And Bone Tissue Necrosis
One factor affecting osseointegration gets almost no attention outside the research literature, and it happens before the patient leaves the chair.
Preparing the implant site means cutting bone, and cutting bone generates heat. Bone cells die at predictable thresholds: roughly seventy degrees Celsius causes immediate damage, and around fifty degrees will do it if sustained for thirty to sixty seconds.
If the bone immediately around the implant site has been thermally damaged during preparation, there are no living cells at the bone implant interface to begin new bone formation. The implant is sitting in a shell of dead bone. Everything downstream, every measurement and every review appointment, is dealing with a problem created in the first few minutes.
This is why the way the osteotomy is prepared matters as much as the implant system that goes into it. Drill design, speed and irrigation all determine how much heat reaches the bone during functional preparation. It is an aspect of implant surgery that is invisible to the patient and rarely discussed, and it is one of the things we pay closest attention to.
What Affects The Success Of Osseointegration?
Several factors affect the success of osseointegration, and they divide into what the patient brings and what the surgery controls.
Patient factors: bone density and bone quality at the implant site, smoking, uncontrolled diabetes, a history of periodontal disease and poor oral health, certain bone medications, and radiation to the jaw.
Surgical factors: accurate three-dimensional planning, atraumatic site preparation, achieving adequate primary stability, avoiding contamination, and not loading the implant beyond what its stability supports.
The patient factors can be assessed and often managed before surgery. The surgical factors are entirely within our control, which is where the responsibility sits. The importance of implant site assessment before any surgery is hard to overstate.

Why Osseointegration Matters For Dental Implant Success
Understanding osseointegration explains why an implant behaves like a natural tooth root rather than an appliance resting on the gum. It transmits chewing forces into the jawbone, which keeps the bone stimulated and slows the bone loss that follows tooth loss. Dentures and dental bridges replace the visible tooth. Only a dental implant replaces the root, and only osseointegration makes that possible.
It is also the reason dental implant procedures cannot be rushed. Bone biology sets the pace, and the concept of osseointegration is what separates a successful dental implant from a fixture sitting in bone.
Speak To A Periodontist
If you are considering dental implants, or you have an implant that does not feel right, we can assess it properly. Our periodontists have placed implants across Manhattan, Nutley, Long Island and Westchester for over twenty years, including a large number of cases referred to us after problems elsewhere.
Call (347) 493-2439 or book a consultation. A 3D CBCT scan is included at your consultation at no charge.
